

 h2>What Amoxicillin Is and How It Treats Ear Infections
Amoxicillin is a penicillin-class antibiotic and the primary first-line treatment for uncomplicated bacterial ear infections, known medically as acute otitis media, in patients who are not allergic to penicillin. It is designed to target specific bacterial pathogens rather than general symptoms, making it a targeted therapy for bacterial infections of the middle ear.
The medication works by killing susceptible bacteria responsible for the infection. Amoxicillin is highly effective because it penetrates middle ear fluid efficiently, reaching the site of the infection in therapeutic concentrations. It is active against the three most common bacteria that cause ear infections: Streptococcus pneumoniae, Haemophilus influenzae, and Moraxella catarrhalis. Clinical studies indicate that approximately 85% of bacteria isolated from ear infections are susceptible to amoxicillin, making it a reliable choice for initial treatment.
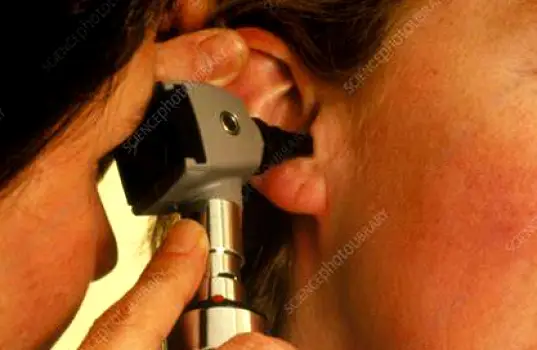
Amoxicillin does not treat viral infections. Many ear infections, particularly those associated with colds or upper respiratory viruses, are caused by viruses rather than bacteria. Because antibiotics have no effect on viruses, amoxicillin provides no benefit in these cases. Healthcare providers must determine whether an ear infection is bacterial or viral through physical examination, typically using an otoscope to view the eardrum and middle ear. Treatment with amoxicillin is only appropriate when a bacterial cause is identified or strongly suspected based on clinical guidelines.
When Amoxicillin Is Recommended for Ear Infections
Amoxicillin is the standard first-choice antibiotic for treating bacterial ear infections in patients without a penicillin allergy. Healthcare providers base the decision to prescribe this medication on specific clinical criteria, including the severity of symptoms, the patient's age, and how long the symptoms have persisted. Diagnosis requires a physical examination to view the eardrum and confirm inflammation or fluid buildup in the middle ear.
The medication is typically recommended for moderate to severe cases of acute otitis media. Specific scenarios where amoxicillin is usually prescribed include infants aged 6 months or younger, regardless of symptom severity. For children between 6 months and 2 years, it is prescribed when moderate to severe ear pain is present. Children aged 2 years or older are generally prescribed amoxicillin if they have a fever of 102.2°F (39°C) or higher.
Severe symptoms also warrant immediate antibiotic treatment. These include ear drainage, high fever, or noticeable hearing loss. If symptoms persist for more than 2 to 3 days without improvement, healthcare providers are more likely to recommend amoxicillin to prevent complications and accelerate recovery.
Certain medical conditions increase the risk of complications from ear infections. Children with cleft palate, Down syndrome, immune system disorders, or cochlear implants are more likely to be prescribed antibiotics promptly. These populations are considered higher risk due to potential difficulties in healing or increased susceptibility to severe outcomes.
Treatment approaches differ for adults. Adult ear infections are less likely to resolve spontaneously without intervention. Healthcare providers tend to prescribe antibiotics sooner for adults than for children. Observational data suggests that oral antibiotics, including amoxicillin, are prescribed in approximately 46% of acute otitis media episodes in adults, reflecting a lower threshold for treatment compared to pediatric cases.
Amoxicillin and Ear Infections
When Antibiotics May Not Be Necessary
Many ear infections do not require antibiotic treatment because they are caused by viruses or resolve on their own. Amoxicillin and other antibiotics target bacteria exclusively and have no effect on viral pathogens. If an ear infection is viral, antibiotic treatment provides no benefit and may expose the patient to unnecessary side effects.
Healthcare providers often employ a watchful-waiting approach for specific patient groups. This strategy is typically recommended for children over 6 months of age who present with mild symptoms. Criteria for this approach include mild ear pain, the absence of fever, and a symptom duration of less than 48 hours. In many of these mild cases, the infection resolves without antibiotics within 2 to 3 days as the body's immune system clears the issue.
Distinguish between treating the infection and managing pain. Antibiotics do not directly relieve ear pain; they work by eliminating the underlying bacteria, a process that takes time. For immediate comfort, analgesics such as acetaminophen or ibuprofen are used. These pain relievers typically begin working within 30 to 45 minutes, providing symptom relief while the body handles the infection or while antibiotics take effect if they are prescribed.
The approach to treatment differs between children and adults. While watchful waiting is a common and accepted practice for mild pediatric cases, adults are less likely to be observed without treatment. Adult ear infections are less prone to spontaneous resolution, so healthcare providers generally prescribe antibiotics sooner for adults than for children. This distinction ensures that adults receive timely care while preventing antibiotic overuse in children whose mild infections may clear independently.
Amoxicillin Dosage and Treatment Duration
Amoxicillin dosing is individualized based on a patient's age, body weight, the severity of the infection, and overall immune status. Healthcare providers calculate specific amounts to ensure therapeutic levels are reached in the middle ear fluid while minimizing the risk of side effects.
For children weighing 40 kilograms (approximately 88 pounds) or less, the typical dosage ranges from 20 to 40 milligrams per kilogram of body weight per day. This total daily amount is usually divided into smaller doses administered every 8 hours. This divided dosing schedule helps maintain consistent antibiotic levels in the bloodstream. Children who weigh more than 40 kilograms are generally transitioned to the standard adult dosing regimen.
Adults typically receive a dosage of 250 milligrams taken three times daily, or 875 milligrams taken twice daily. The choice between these regimens depends on the prescribing clinician's preference and the specific clinical context.
The standard treatment duration for acute ear infections is typically 7 to 10 days. Complete the entire prescribed course of medication, even if symptoms improve significantly within the first few days. Stopping the antibiotic early can leave surviving bacteria in the ear, which may lead to a recurrence of the infection. Incomplete treatment contributes to the development of antibiotic-resistant bacteria, making future infections harder to treat with standard therapies. Healthcare providers may adjust the duration or dosage based on the patient's response to treatment or if complications arise.
How Quickly Amoxicillin Works for Ear Pain and Infection
Most people experience meaningful symptom improvement within 1 to 2 days of starting amoxicillin treatment for a bacterial ear infection. This timeline reflects the medication's ability to rapidly reduce the bacterial load in the middle ear. As the antibiotic eliminates susceptible pathogens, the resulting inflammation and pressure behind the eardrum begin to subside, leading to noticeable relief.
Distinguish between pain relief and the resolution of the infection itself. Amoxicillin does not act as a direct painkiller. It alleviates pain indirectly by treating the underlying bacterial cause. The reduction in bacterial activity decreases swelling and fluid buildup, which are the primary sources of discomfort. For immediate pain management during the initial days of treatment, analgesics such as acetaminophen or ibuprofen are often recommended, as they begin working within 30 to 45 minutes.
While pain typically improves within the first couple of days, other symptoms may persist longer. A blocked, full, or muffled sensation in the ear is common even after the infection has cleared. This occurs because sterile fluid can remain in the middle ear for weeks after the bacteria have been eliminated. The fluid gradually drains or is absorbed by the body, so temporary hearing changes or aural pressure are normal parts of the recovery process and do not necessarily indicate treatment failure.
Monitoring the response to amoxicillin is critical. If there is no improvement after 48 to 72 hours, the patient should contact their healthcare provider. Lack of improvement suggests that the bacteria may be resistant to amoxicillin, that the infection is viral rather than bacterial, or that a different complication is present. In these cases, alternative antibiotics or further clinical evaluation are typically required to ensure proper recovery.
Common Side Effects and Safety Considerations
Amoxicillin is generally well-tolerated, but like all medications, it can cause adverse reactions. Understanding these potential side effects helps patients monitor their response to treatment and identify when to seek medical attention.
Common side effects are typically mild and gastrointestinal in nature. The most frequently reported issues include diarrhea, nausea, and vomiting. These symptoms occur because antibiotics can disrupt the natural balance of bacteria in the digestive tract. Patients may also experience skin rashes or develop yeast infections, particularly in moist areas of the body. These reactions are often manageable with supportive care, such as staying hydrated or using over-the-counter remedies for diarrhea, though patients should always consult their healthcare provider before adding other medications to their regimen.
While less common, serious risks require immediate attention. Allergic reactions to amoxicillin range from mild hives to severe, life-threatening anaphylaxis. Symptoms of a severe allergic reaction include difficulty breathing, swelling of the face or throat, and rapid heartbeat. Any signs of an allergic response warrant stopping the medication and seeking emergency medical care.
Another significant, though rare, risk is Clostridioides difficile (C. diff) infection. Antibiotics can allow this specific bacterium to overgrow in the gut, leading to severe diarrhea, abdominal pain, dehydration, and gut inflammation. C. diff infection often requires specific treatment and, in severe cases, hospitalization. Patients who experience watery or bloody diarrhea, especially if accompanied by fever or cramping, should contact their healthcare provider promptly.
The misuse or unnecessary use of antibiotics contributes to the broader public health crisis of antibiotic resistance. When amoxicillin is used incorrectly-for example, for viral infections or by stopping the course early-bacteria can evolve to withstand the drug's effects. This makes future bacterial infections harder to treat with standard antibiotics. To maintain the effectiveness of amoxicillin for those who need it, the medication should only be used as prescribed by a healthcare professional, for the specific duration indicated, and for confirmed or strongly suspected bacterial infections.
Who Should Not Take Amoxicillin
The primary contraindication for amoxicillin is a known allergy to penicillin or other beta-lactam antibiotics. Amoxicillin belongs to the penicillin class of drugs, and individuals with a history of allergic reactions to penicillins are at risk of experiencing similar or potentially more severe allergic responses if exposed to this medication.
Patients with a documented penicillin allergy should not take amoxicillin. Allergic reactions can range from mild skin rashes and hives to severe, life-threatening conditions such as anaphylaxis, which involves difficulty breathing, swelling of the throat or face, and a drop in blood pressure. Anyone who has previously experienced an allergic reaction to penicillin must avoid amoxicillin entirely.
For patients with a known severe penicillin allergy, healthcare providers will prescribe alternative antibiotics. Options such as azithromycin or cefdinir are commonly used as substitutes for treating bacterial ear infections in these patients. Disclose any history of drug allergies to the prescribing clinician before starting treatment to ensure a safe and effective therapeutic alternative is selected.
Beyond allergy history, healthcare providers carefully evaluate a patient's overall medical profile before prescribing amoxicillin. This includes reviewing recent antibiotic use, as prior exposure can influence the likelihood of treatment failure or resistance. Other medical conditions, such as kidney disease or mononucleosis, may also affect dosing decisions or safety considerations. Healthcare providers integrate this full medical context to determine whether amoxicillin is the appropriate choice or if a different treatment strategy is necessary.
Alternative Antibiotics and Treatments
When amoxicillin is not suitable or effective, healthcare providers have several alternative antibiotics and treatment strategies. The choice of alternative depends on the patient's allergy history, the severity of the infection, and whether previous treatments have failed.
For patients with a penicillin allergy, amoxicillin is contraindicated. In these cases, providers typically prescribe alternative antibiotics such as azithromycin or cefdinir. These medications provide effective coverage against common ear infection bacteria without triggering the allergic reaction associated with penicillin. Selecting the correct alternative requires a thorough review of the patient's allergy history to ensure safety.
If amoxicillin fails to improve symptoms within 48 to 72 hours, or if the patient has recently taken amoxicillin, providers may switch to amoxicillin-clavulanate (Augmentin). This combination antibiotic is more effective against certain bacteria, specifically Haemophilus influenzae and Moraxella catarrhalis, which can produce enzymes that degrade standard amoxicillin. It is also the preferred choice for recurrent ear infections or cases where resistant bacteria are suspected.
For children who are vomiting and cannot tolerate oral medications, ceftriaxone may be administered as an injection. This ensures the patient receives the necessary antibiotic dose even if they cannot keep oral pills or liquid down. Topical antibiotic ear drops, such as ciprofloxacin, are used for outer ear infections (swimmer's ear) rather than middle ear infections, as they cannot effectively penetrate the eardrum to reach the site of acute otitis media.
Pain management remains a critical component of treatment regardless of the antibiotic choice. Acetaminophen and ibuprofen are commonly recommended to relieve ear pain and fever. These analgesics work independently of the antibiotic to provide comfort while the medication addresses the underlying infection. For individuals with recurrent ear infections that do not respond well to medication, surgical intervention with ear tubes may be recommended. Ear tubes help ventilate the middle ear and prevent fluid buildup, reducing the frequency and severity of future infections.
Preventing Ear Infections
Reducing the risk of ear infections involves a combination of vaccination, hygiene practices, and environmental management. Several evidence-based strategies can significantly lower the likelihood of developing acute otitis media, particularly in children who are most susceptible to these infections.
Vaccination is one of the most effective preventive measures. Keeping childhood vaccinations up to date, specifically the pneumococcal and influenza vaccines, helps protect against the bacterial and viral pathogens that frequently lead to ear infections. These vaccines reduce the incidence of the respiratory illnesses that often precede ear infections.
Hygiene and environmental factors also play a critical role. Frequent handwashing reduces the spread of viruses and bacteria that cause upper respiratory infections, which are common precursors to ear infections. Breastfeeding for at least the first six months of life has been associated with a reduced risk of ear infections in infants, likely due to the immune benefits provided by breast milk.

Environmental exposures can increase susceptibility. Exposure to secondhand smoke irritates the Eustachian tubes and impairs their ability to drain fluid, increasing the risk of infection. Avoiding smoke exposure helps maintain healthy ear function. Proper ear care after swimming, such as drying the ears thoroughly, helps prevent outer ear infections, known as swimmer's ear. Avoiding the insertion of cotton swabs or other objects into the ear canal protects the ear canal from injury and infection.
Managing underlying health conditions is another key preventive strategy. Allergies and upper respiratory infections can cause swelling and blockage of the Eustachian tubes, leading to fluid buildup in the middle ear. Effectively managing these conditions helps prevent the blockage that creates an environment conducive to bacterial growth. By reducing the frequency of ear infections, these preventive measures also help reduce the need for antibiotic treatment, contributing to better overall antibiotic stewardship.